


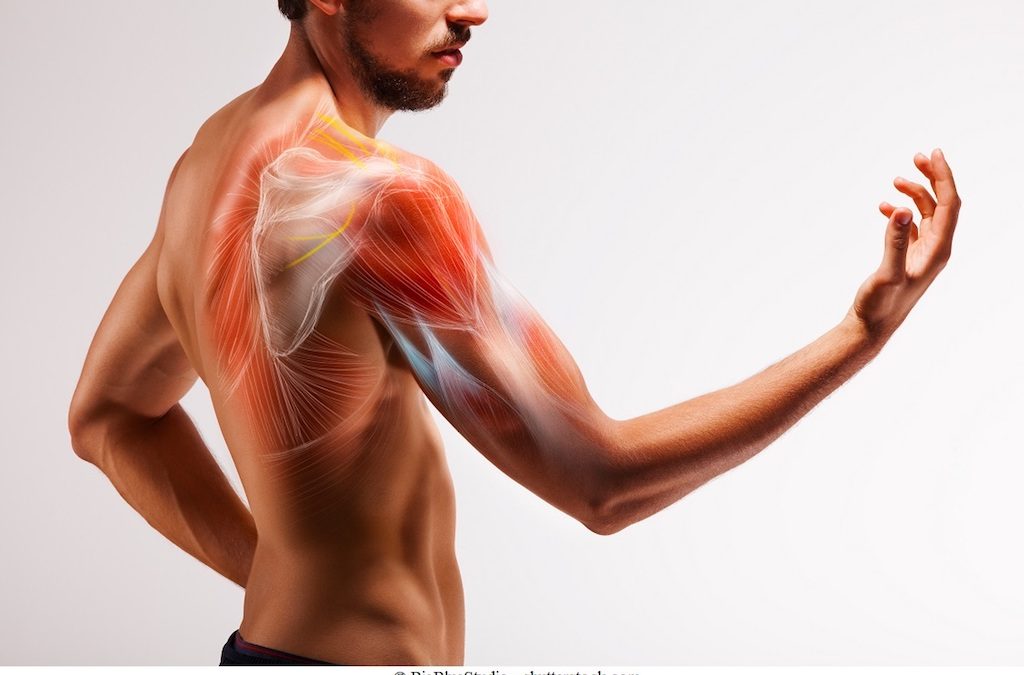
The shoulder is the most mobile joint in the body. Because of its wide range of motion, it is susceptible to injury and pain. The shoulder may hurt after sustaining an injury or for no apparent reason. Although most shoulder problems are relatively short-lived, pain is sometimes indicative of a more complex problem. Here is a guide to what might be wrong and whether or not it is cause for concern.
Don’t worry:
Mild pain with elevation and when playing sports is common. The four tendons that make up the rotator cuff and biceps tendon (the combined muscles that drive shoulder movements) can be inflamed by activities such as throwing, shooting hoops, and lifting weights. The tendons are covered by a thin layer called bursa, which swells when irritated. The resulting bursa is full of inflammatory components that irritate nerve fibers, sending pain signals to the brain. Elimination of these activities and occasional use of anti-inflammatories usually cures mild bursitis or tendonitis and resolves the problem.
Exercises to strengthen posture are also commonly used by our physical therapists to correct mild shoulder irritation. Lying down at the desk, reaching for the mouse, leaning over the keyboard can put a strain on the shoulder, neck, or back, and can be the cause of shoulder pain.
What to do:
Shoulder-specific exercises begin with correcting posture. Stand with your shoulders behind and in front of your hips with your belly button tucked in and notice the difference. By squeezing your shoulder blades repetitively throughout the day, with your stomach in and your head up, you can correct your posture and relieve mild impingement pain. Perform all shoulder exercises with your hands below shoulder level, then use free weights and resistance cords for internal and external strengthening exercises, including biceps curls and triceps thrusts.
More concern:
Pain that does not go away or pain that occurs with every activity indicates that key tissues are irritated enough to send pain signals even without movement. This degree of inflammation precedes more structural injuries, such as tissue tears or early arthritis. Treated early, rotator cuff tears and eventual arthritis can be prevented. Treatments are often injections of growth factors from platelets, amniotic fluid, and lubrication with hyaluronic acid. Physical therapy focuses on shoulder mechanics, muscle strengthening, and sport-specific training to help correct the activity that may be causing the injury. We often see pitchers with slight errors in their throwing mechanics or golfers with swing abnormalities that cause problems. Correcting the pitching or swing corrects the pain.
We avoid cortisone injections, as there is clear evidence that it weakens shoulder tissues if used too frequently. Pain can also be generated by shoulder instability, where the shoulder moves abnormally on the face of the glenoid. While this may be genetic in origin, it is most commonly due to an injury to the labrum or joint seal.
What to do:
Persistent pain requires a complete examination, x-rays, and an MRI. While an ultrasound examination can also add information, nothing gives a more complete picture than an examination with X-rays and MRI. Once a definitive diagnosis is made, targeted therapy can begin. It is sad to see small lesions spread to more serious ones because of the lack of an accurate diagnosis. For inflammation and even small tears, injections of biologic therapies combined with specific shoulder exercises can be curative. For labrum and rotator cuff tears, it is necessary to choose carefully which one should be repaired and how the repair is done.
A real concern:
Pain at night or pain that does not improve with therapy after four weeks are red flags. Pain that radiates down the arm or to the neck or back is also worrisome and may indicate injury not only to the shoulder but sometimes to the neck. It may originate in the discs in the neck or nerves in the front of the shoulder called the brachial plexus. These injuries should be treated with thorough physical examinations, X-rays and MRIs. Shoulder instability, with the shoulder entering or leaving the joint, is another area that is best treated with early repair of torn ligaments.
A complete rotator cuff tear often presents with nocturnal pain because when you tip over, you push your arm up into the socket through the rotator cuff tear. Rotator cuff tears are divided into two main groups: acute and degenerative tears. Acute tears in healthy tissue, when small, can be treated with injections and time. Larger ones, on the other hand, are almost always surgically repaired. Degenerative tears that have been present for a long time and are often associated with some degree of arthritis fall into a more nuanced decision tree. Some should clearly be repaired. In others, however, the rate of repair failure is high enough that nonsurgical treatment is best. After repair, the patient should be ready for a painful three-month rehabilitation course, with full recovery achieved after a year of exercise.
What to do:
Diagnose and treat early. Fortunately, most torn tissue problems in the shoulder can be repaired under a local block with an arthroscope as an outpatient procedure. Only the most severe cases of arthritis require bionic (artificial) replacement. Biologic treatments using anabolic tissue stimulation with injections, exercise, physical therapy, and activity coaching are becoming more effective, more targeted, and more widespread. The key is to treat them early before complete tissue tearing leads to disability.